Follow us
Add us as a preferred source on Google
Subscribe to our newsletter
Actor Christina Applegate was diagnosed with multiple sclerosis (MS) over five years ago — but this week, she announced that a recent reevaluation found that she doesn’t have the condition after all. In the wake of that revelation, she’s been left without a diagnosis, and she said on a podcast that she felt she was “back at square one, where I don’t know what’s going on with me.”
Applegate’s case is not totally unique, although MS diagnosis has improved over the years. Studies offer different estimates of how frequently MS is misdiagnosed, with rates ranging from 5% to over 40%, depending on the patient population and clinical setting. There is also some degree of underdiagnosis — cases in which people with MS aren’t flagged as having the disease.
So, how difficult is MS to identify, and what does that mean for patients? Live Science spoke with experts about the current state of MS diagnostics and the improvements that may be coming in the future.
“It’s also really important that doctors and patients be aware that it’s not inappropriate to revisit a diagnosis — to make sure it’s right,” Dr. Ari Green, chief of the Division of Neuroimmunology and Glial Biology at the University of California, San Francisco, told Live Science.
The importance of early diagnosis
MS is an autoimmune disorder in which the immune system attacks the central nervous system, meaning the brain and spinal cord. These attacks harm neurons directly and also take aim at myelin — a fatty, insulating substance that coats neurons’ outgoing wires and helps them send signals efficiently.
This damage leads to distinctive scarring in nerve tissue and causes a range of symptoms, including vision problems, muscle weakness, tingling sensations, dizziness and bladder control issues. Patients with untreated and advanced MS can lose the ability to walk and stand or, in some cases, develop partial or complete paralysis.
You’re trying to be as proactive as possible with this.
Dr. Yohance Allette, a neuroimmunologist and researcher at Penn State Health
These severe outcomes are becoming rarer as treatments have improved significantly, Green said. Current treatments keep immune attacks at bay and thus prevent further nerve damage.
“It’s moved from people ending up with severe, profound disability at 10 or 20 years of disease, and now it’s at like 30 or 40 years of disease, they have modest disability,” Green told Live Science. The disease most often emerges between age 20 and 40, although it can occur in any age group. Importantly, Green said, “the earlier people initiate treatment who have MS, the better they do over the long term.”
For that reason, it’s important to reach an MS diagnosis efficiently, so that patients can start that critical treatment, said Dr. Yohance Allette, a neuroimmunologist and researcher at Penn State Health. “You’re trying to be as proactive as possible with this.”
“A diagnosis of exclusion”
However, there is no single, surefire test that can reliably show that a person has MS. “With MS, it comes down to the keyword ‘criteria,” Allette said.
MS experts have compiled a list of criteria, which are updated periodically, that reflect how the features of MS show up in lab tests; brain, optic nerve and spinal cord scans; and patients’ symptoms. (Green was among the dozens of experts involved in the latest update, which was conducted in 2024 and published in 2025.)
So, what does diagnosis look like for a patient today? The first step is to recognize symptoms that might point to MS.
Those early symptoms — such as issues with balance, vision or bowel control — vary significantly from person to person and may not immediately raise red flags that the patient has a neurological problem, Green said. The way those symptoms emerge can be a clue, though; typically, MS symptoms worsen over the course of a day or a few days and then dissipate, he noted.
Once concerning symptoms are flagged, MRIs of the brain and spinal cord are taken. The scans may reveal evidence of myelin damage, and neurologists note the shape, size and location of those lesions. Damage often appears near blood vessels, since that’s where immune cells access the brain, Green noted.
Other conditions — like migraine, uncontrolled diabetes or vascular disease — can also come with some myelin damage, so it’s key to look for specific patterns related to MS. Neurologists who specialize in MS are practiced at this task, while doctors in other neurological specialties may not know how to distinguish MS-related myelin damage from that caused by other conditions, Allette and Green both noted.
Myelin (yellow) helps neurons send messages efficiently. In MS, the immune system attacks myelin, causing it to break down.
(Image credit: koto_feja via Getty Images)
MRIs of the optic nerves can also show MS-related damage, and these scans are emphasized in the latest diagnostic criteria, Allette noted. Electrophysiologic tests, which assess the function of nerves, are also “super important because they tell you something totally different than just seeing a lesion on MRI,” Green said. Further signs of MS can be found via spinal taps, which sample the fluid around the brain and spinal cord that may carry proteins and inflammatory cells related to MS.
In addition to collecting these clues, doctors must rule out diseases that look similar to MS. These include neuromyelitis optica and myelin oligodendrocyte glycoprotein antibody-associated disease (MOGAD) — two other autoimmune conditions that affect the central nervous system. Both these diseases are associated with distinctive, rogue immune proteins, called autoantibodies, that latch onto various parts of the nervous system; those specific antibodies are not seen in MS.
Other conditions — such as the inflammatory disease lupus and neuromuscular disease myasthenia gravis — can sometimes look like MS at first glance, as well. Some of these “MS mimics” can be ruled out with data from spinal taps or antibody tests, while others require a more laborious battery of assessments.
“Ultimately, it’s a diagnosis of exclusion,” Allette said. “There are things that you can rule out quickly,” while others take time to investigate thoroughly.
Conditions like MOGAD and neurosarcoidosis, an inflammatory condition sometimes mistaken for MS, can actually be worsened by MS medications, Green noted. So if a patient’s MS flare-ups worsen after they start a treatment, that could hint that something else is the culprit, he said. But because there may be long gaps between flare-ups, doctors may need to track a patient for some time before their worsening becomes apparent.
Gaps to fill?
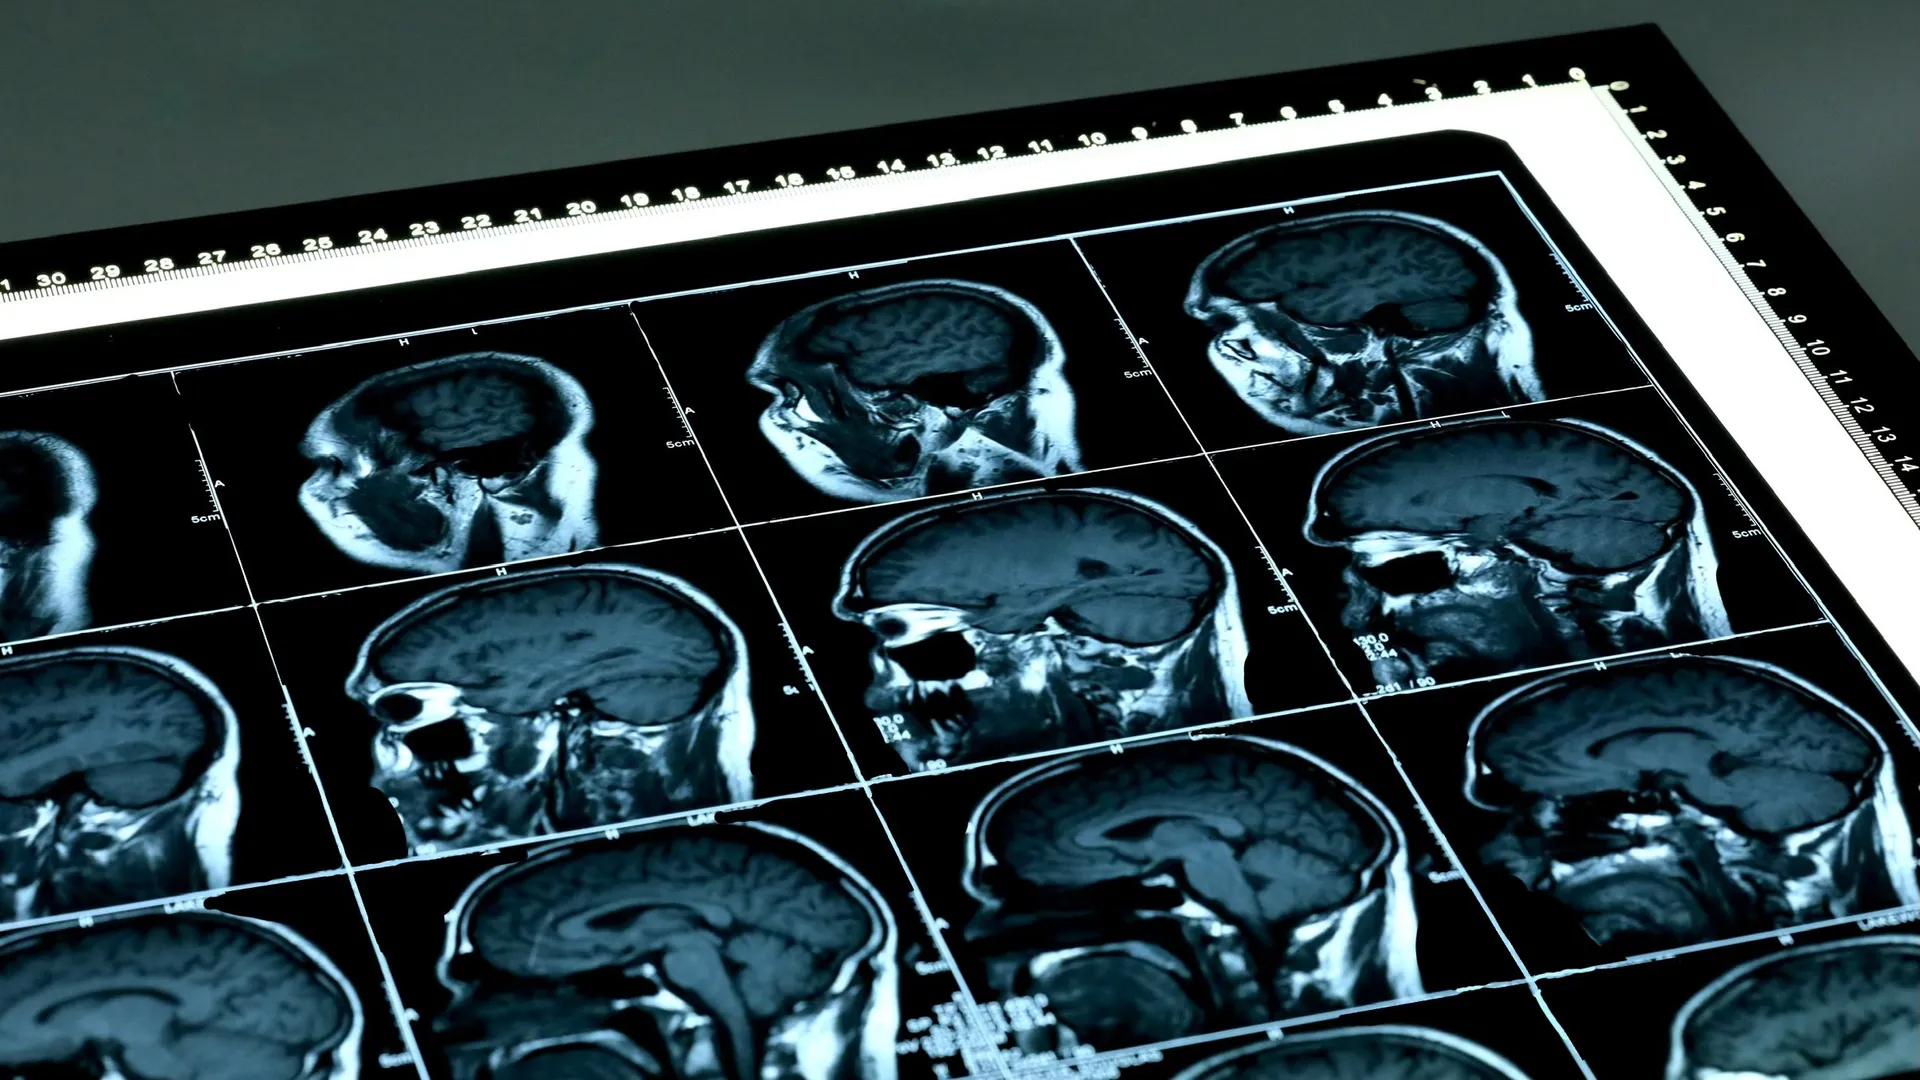
The updated diagnostic criteria for MS include new guidelines for how to examine brain MRIs. These criteria could likely be improved even more in future, Green noted.
(Image credit: Douglas Sacha via Getty Images)
Given all the tools available, a patient can be reasonably confident in their MS diagnosis, Green said.
“In general, there’s a fair amount of diagnostic confidence that comes with MS diagnosis today,” he said. However, that confidence is highest when the tools are in the hands of a specialist who is following the most up-to-date criteria, he noted. The test results require interpretation, and that’s one place where uncertainty can creep in.
Regarding Applegate’s circumstances, “to speak bluntly, I think the case came as a bit of a shock because we always expect that part of society to have quick access [to high-quality medical care],” Allette said. For some patients, the road to accessing specialty MS care can be long, which can result in missteps, and even misdiagnoses, along the way. Applegate went five years with an incorrect diagnosis, but “would that have been seven or eight years for somebody who doesn’t have that access?” Allette speculated.
Without knowing the details of Applegate’s case, Allette and Green said it would be difficult to speculate on what resulted in her misdiagnosis. (Applegate mentioned that her brain scans had been reassessed with a “new technology,” but didn’t go into specifics.)
Looking toward the future of MS diagnostics, Green and Allette think emerging proteomic tests hold a lot of promise. Such tests generate a profile of the proteins and smaller fragments, called peptides, in a patient’s blood or cerebrospinal fluid. They can be designed to look for proteins involved in driving the underlying immune attacks, as well as signs of nerve damage that MS wrecks, they explained.
Exclusive to Live Science Pro
These in-depth, protein analyses could help paint a more comprehensive picture of MS, which could ultimately help scientists “look at that whole system in concert” to reach a strong diagnosis, Allette said.
No proteomics-based diagnostic tests for MS have been approved yet, Green clarified. And even with those upcoming advances, Green doubts there will ever be a simple, one-time test that can determine a patient has MS. “I think that’s probably unlikely, that it would ever be that straightforward,” he said.
He does think that, in time, scientists could pare down the number of tests required to reach a diagnosis, but he argued that the clinical evaluation conducted by a neurologist will likely remain crucial. “I’m doubtful that there’s going to be a test that will fully replace that,” he said, “at least in the foreseeable future.”
Help us improve Live Science Pro: We’re always trying to make our content better. Leave us feedback about Pro here.